
Science
Our drug candidate EL 924 designed to Address Unmet Needs in the Global Obesity and Insulin Resistance Epidemic
The Challenge
THE NEXT FRONTIER IN OBESITY TREATMENT IS SUSTAINABILITY
EFFICACY IS NO LONGER ENOUGH
The Most Effective Drug Is the One Patients Are Willing to Keep Taking
GLP-1/GIP therapies transformed obesity treatment yet ~35% were no longer persistent at 1 year in real-world use
TIRZEPATIDE
~21% mean weight loss
4–7% discontinued due to adverse events in SURMOUNT-1
~35% were no longer persistent at 1 year in real-world use
RETATRUTIDE
~28% mean weight loss
Yet up to 11% discontinued due to adverse events in TRIUMPH-1
Efficacy keeps improving. The sustainability challenge remains.
For a chronic therapy, long-term persistence may ultimately depend on the balance between two simple questions:
1. DO I LIKE WHAT THIS DRUG DOES FOR ME?
GLP-1 → YES
2. DO I LIKE HOW I FEEL WHILE TAKING IT?
GLP-1 → NOT ALWAYS
GI effects • appetite suppression • food enjoyment • nutrition • physical function • social life • overall treatment burden
Patients may value the results of treatment while not wanting to live with the treatment experience indefinitely.
A next-generation obesity therapy that delivers more weight loss without improving that experience may not solve the problem that remains.
THE NEXT FRONTIER: YES + YES
Do I like what it does for me? → YES
Do I like how I feel while taking it? → YES
As efficacy approaches increasingly high levels, the next generation may not need to win by producing the most weight loss.
It may win by making effective treatment something patients are willing to live with long term.
Our approach and biologic basis for EL 924:
Mimicking the Profound Metabolic Benefits of Bariatric Surgery with a Simple Oral Therapy:
A Novel Approach to Obesity Beyond Appetite Suppression
The Intestine as a Master Regulator of Metabolic Health and Obesity
The Biological Foundation
Metabolic surgeries such as gastric bypass can produce profound and rapid improvements in insulin resistance, diabetes, broader metabolic health, and obesity. Importantly, improvements in glucose regulation can occur within days—before substantial weight loss—suggesting that their metabolic effects are not explained by calorie restriction or weight loss alone.
A growing body of evidence points to changes in nutrient flow and intestinal nutrient sensing, together with alterations in bile-acid signaling, gut hormones, and broader gut-derived metabolic signaling. These coordinated changes appear to reshape communication between the intestine and key metabolic organs involved in glucose regulation, insulin sensitivity, energy balance, and body-weight control.
At Elaphron, our approach is designed to engage key aspects of this biology without surgery.
Rethinking Obesity: Metabolic Health First
Metabolic obesity and obesity are not the same.
Metabolic obesity—the cluster of metabolic dysfunction commonly associated with obesity—includes insulin resistance, compensatory hyperinsulinemia, metabolic dyslipidemia, and abnormal visceral and intra-organ fat accumulation.
It frequently accompanies obesity, but the two are biologically distinct. Metabolic dysfunction can occur without obesity—and obesity can occur without overt metabolic dysfunction.
A LARGE POPULATION EXISTS ON BOTH SIDES OF BMI
~20–30% OF NORMAL-WEIGHT ADULTS MAY BE METABOLICALLY UNHEALTHY
Despite normal body weight, a substantial population exhibits metabolic abnormalities associated with increased cardiometabolic risk.
(Zenas-Trujillo et al., 2023; Wildman et al., 2008, Arch Intern Med)
~10–30%+ OF PEOPLE WITH OBESITY MAY BE RELATIVELY METABOLICALLY HEALTHY
(Wang et al., 2023, JAMA Netw Open; Smith et al., 2019, Nat Rev Endocrinol)
METABOLIC PHENOTYPE CAN MATTER MORE THAN BMI ALONE
The distinction is clinically important.
In a meta-analysis of 41 prospective studies involving >4 million people, metabolically unhealthy normal-weight individuals had, compared with metabolically healthy individuals with obesity:
2.37× higher cardiovascular mortality
1.73× higher risk of major cardiovascular events
1.47× higher all-cause mortality
(Putra et al., 2022, Diabetes Metab Syndr)
What is happening metabolically may sometimes be more informative than body weight alone.
METABOLIC DYSFUNCTION MAY ALSO CONTRIBUTE TO WEIGHT DYSREGULATION
Metabolic dysfunction can emerge before, alongside, or after obesity.
Insulin resistance with compensatory hyperinsulinemia, altered nutrient handling and fat partitioning, ectopic fat accumulation, and changes in appetite and nutrient signaling may create biological feedback loops that favor further metabolic and weight dysregulation.
METABOLIC DYSFUNCTION ↔ WEIGHT DYSREGULATION
METABOLIC IMPROVEMENT CAN PRECEDE MAJOR WEIGHT LOSS
Metabolic surgery provides a powerful human precedent.
Following gastric bypass, glucose regulation and insulin sensitivity can improve rapidly—before substantial weight loss occurs—alongside major changes in nutrient flow and gut-derived metabolic signaling.
Patients can become metabolically healthier before becoming substantially lighter.
METABOLIC DYSFUNCTION AS AN INDEPENDENT THERAPEUTIC TARGET
This creates a potential therapeutic opportunity extending beyond weight loss alone:
- Obesity + metabolic dysfunction → target metabolic health alongside weight
- Normal weight + metabolic dysfunction → target metabolic disease even when weight loss is not the objective
- Early metabolic dysfunction → potentially intervene before progressive metabolic and weight dysregulation
Elaphron is investigating whether modifying the intestinal nutrient-sensing interface and gut-derived metabolic signaling can improve metabolic health directly—with weight loss potentially emerging as a downstream consequence.
METABOLIC HEALTH FIRST. WEIGHT LOSS FOLLOWS
EL-924 — Mechanism of Action, Preclinical Efficacy and Early Human Metabolic Observations
Mechanism of Action
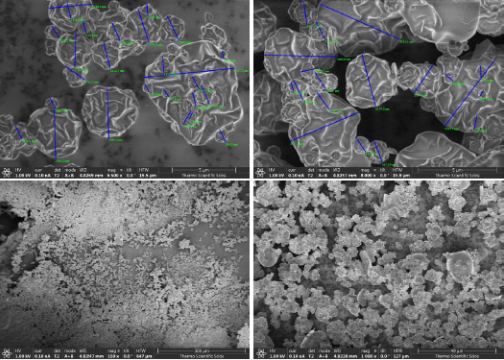
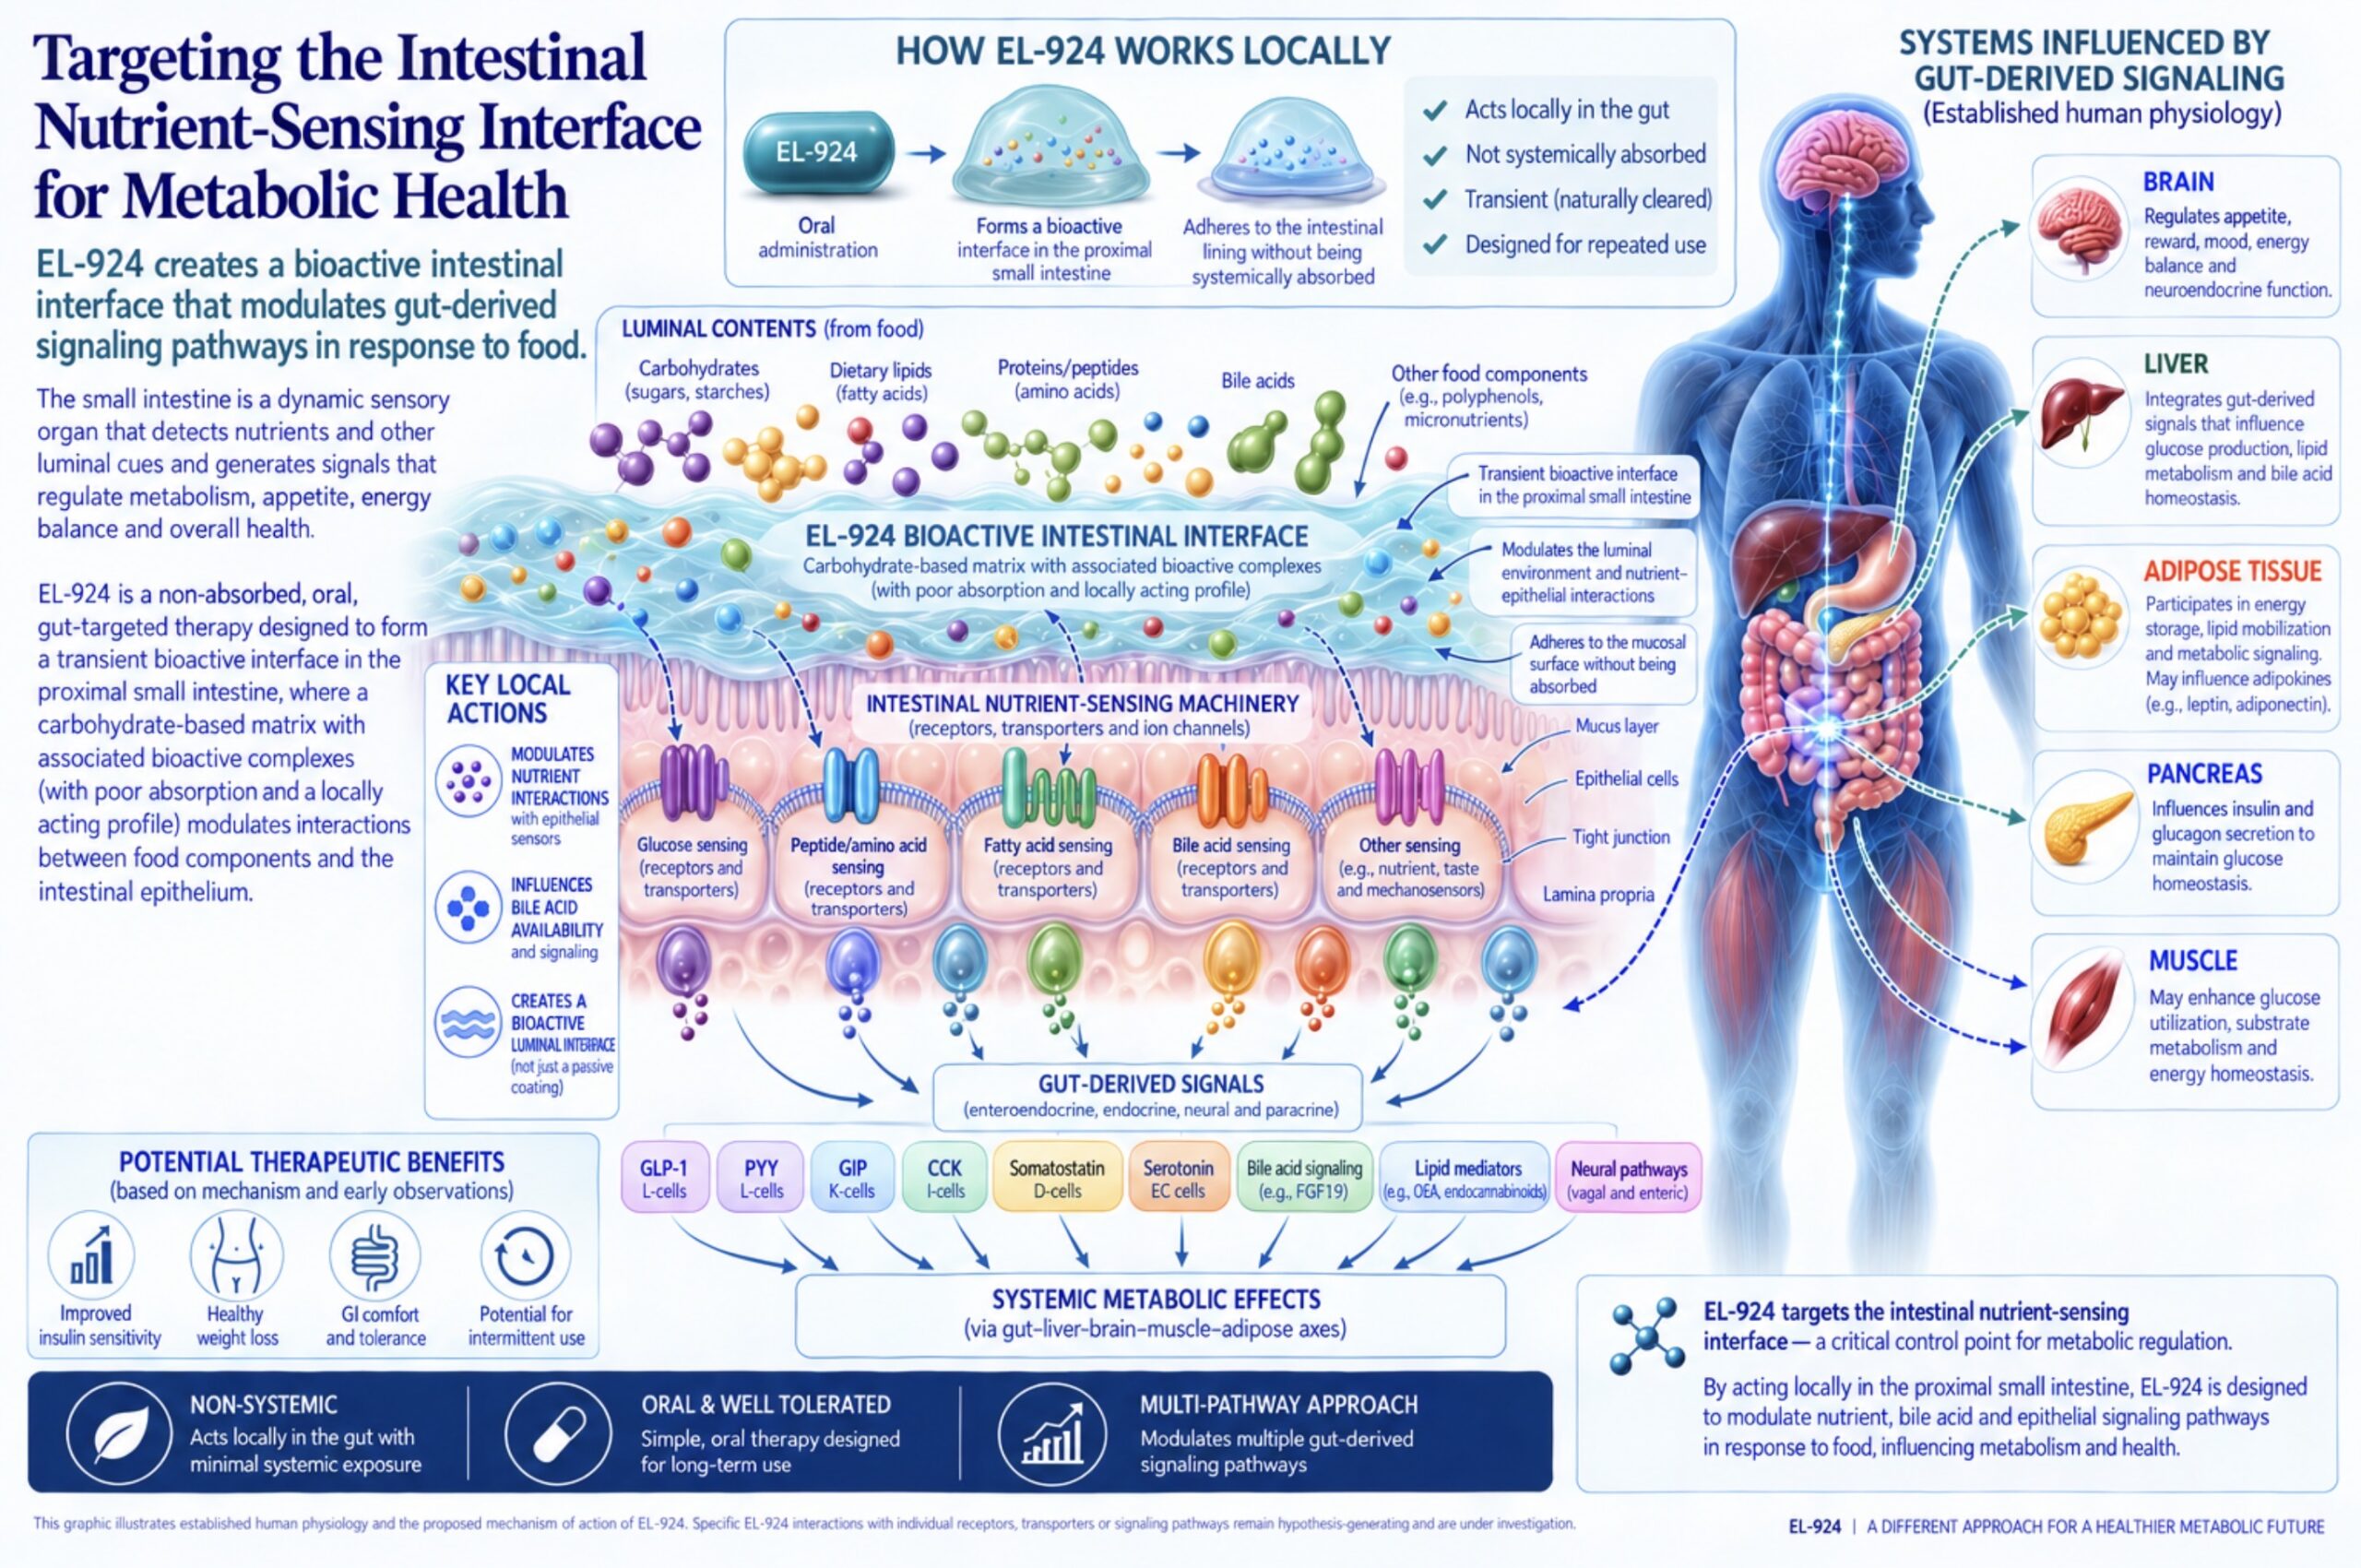
EL-924 is a non-absorbable, locally acting carbohydrate-derived heteropolymer incorporating bioactive coordination complexes selected for their activity, favorable safety profiles, and poor systemic absorption.
After oral administration, EL-924 forms a transient intestinal coating that self-eliminates within hours. The polymer and its associated bioactive complexes create a local interface designed to modulate intestinal receptors, transporters, ion channels, and nutrient- and bile acid–sensing pathways.
By reshaping how the gut responds to food-derived signals, EL-924 is designed to reproduce selected metabolic effects associated with gastric bypass through a non-surgical, gut-localized approach.
Preclinical Obesity Efficacy
Rapid, Reproducible Weight Loss Without Reduced Food Intake
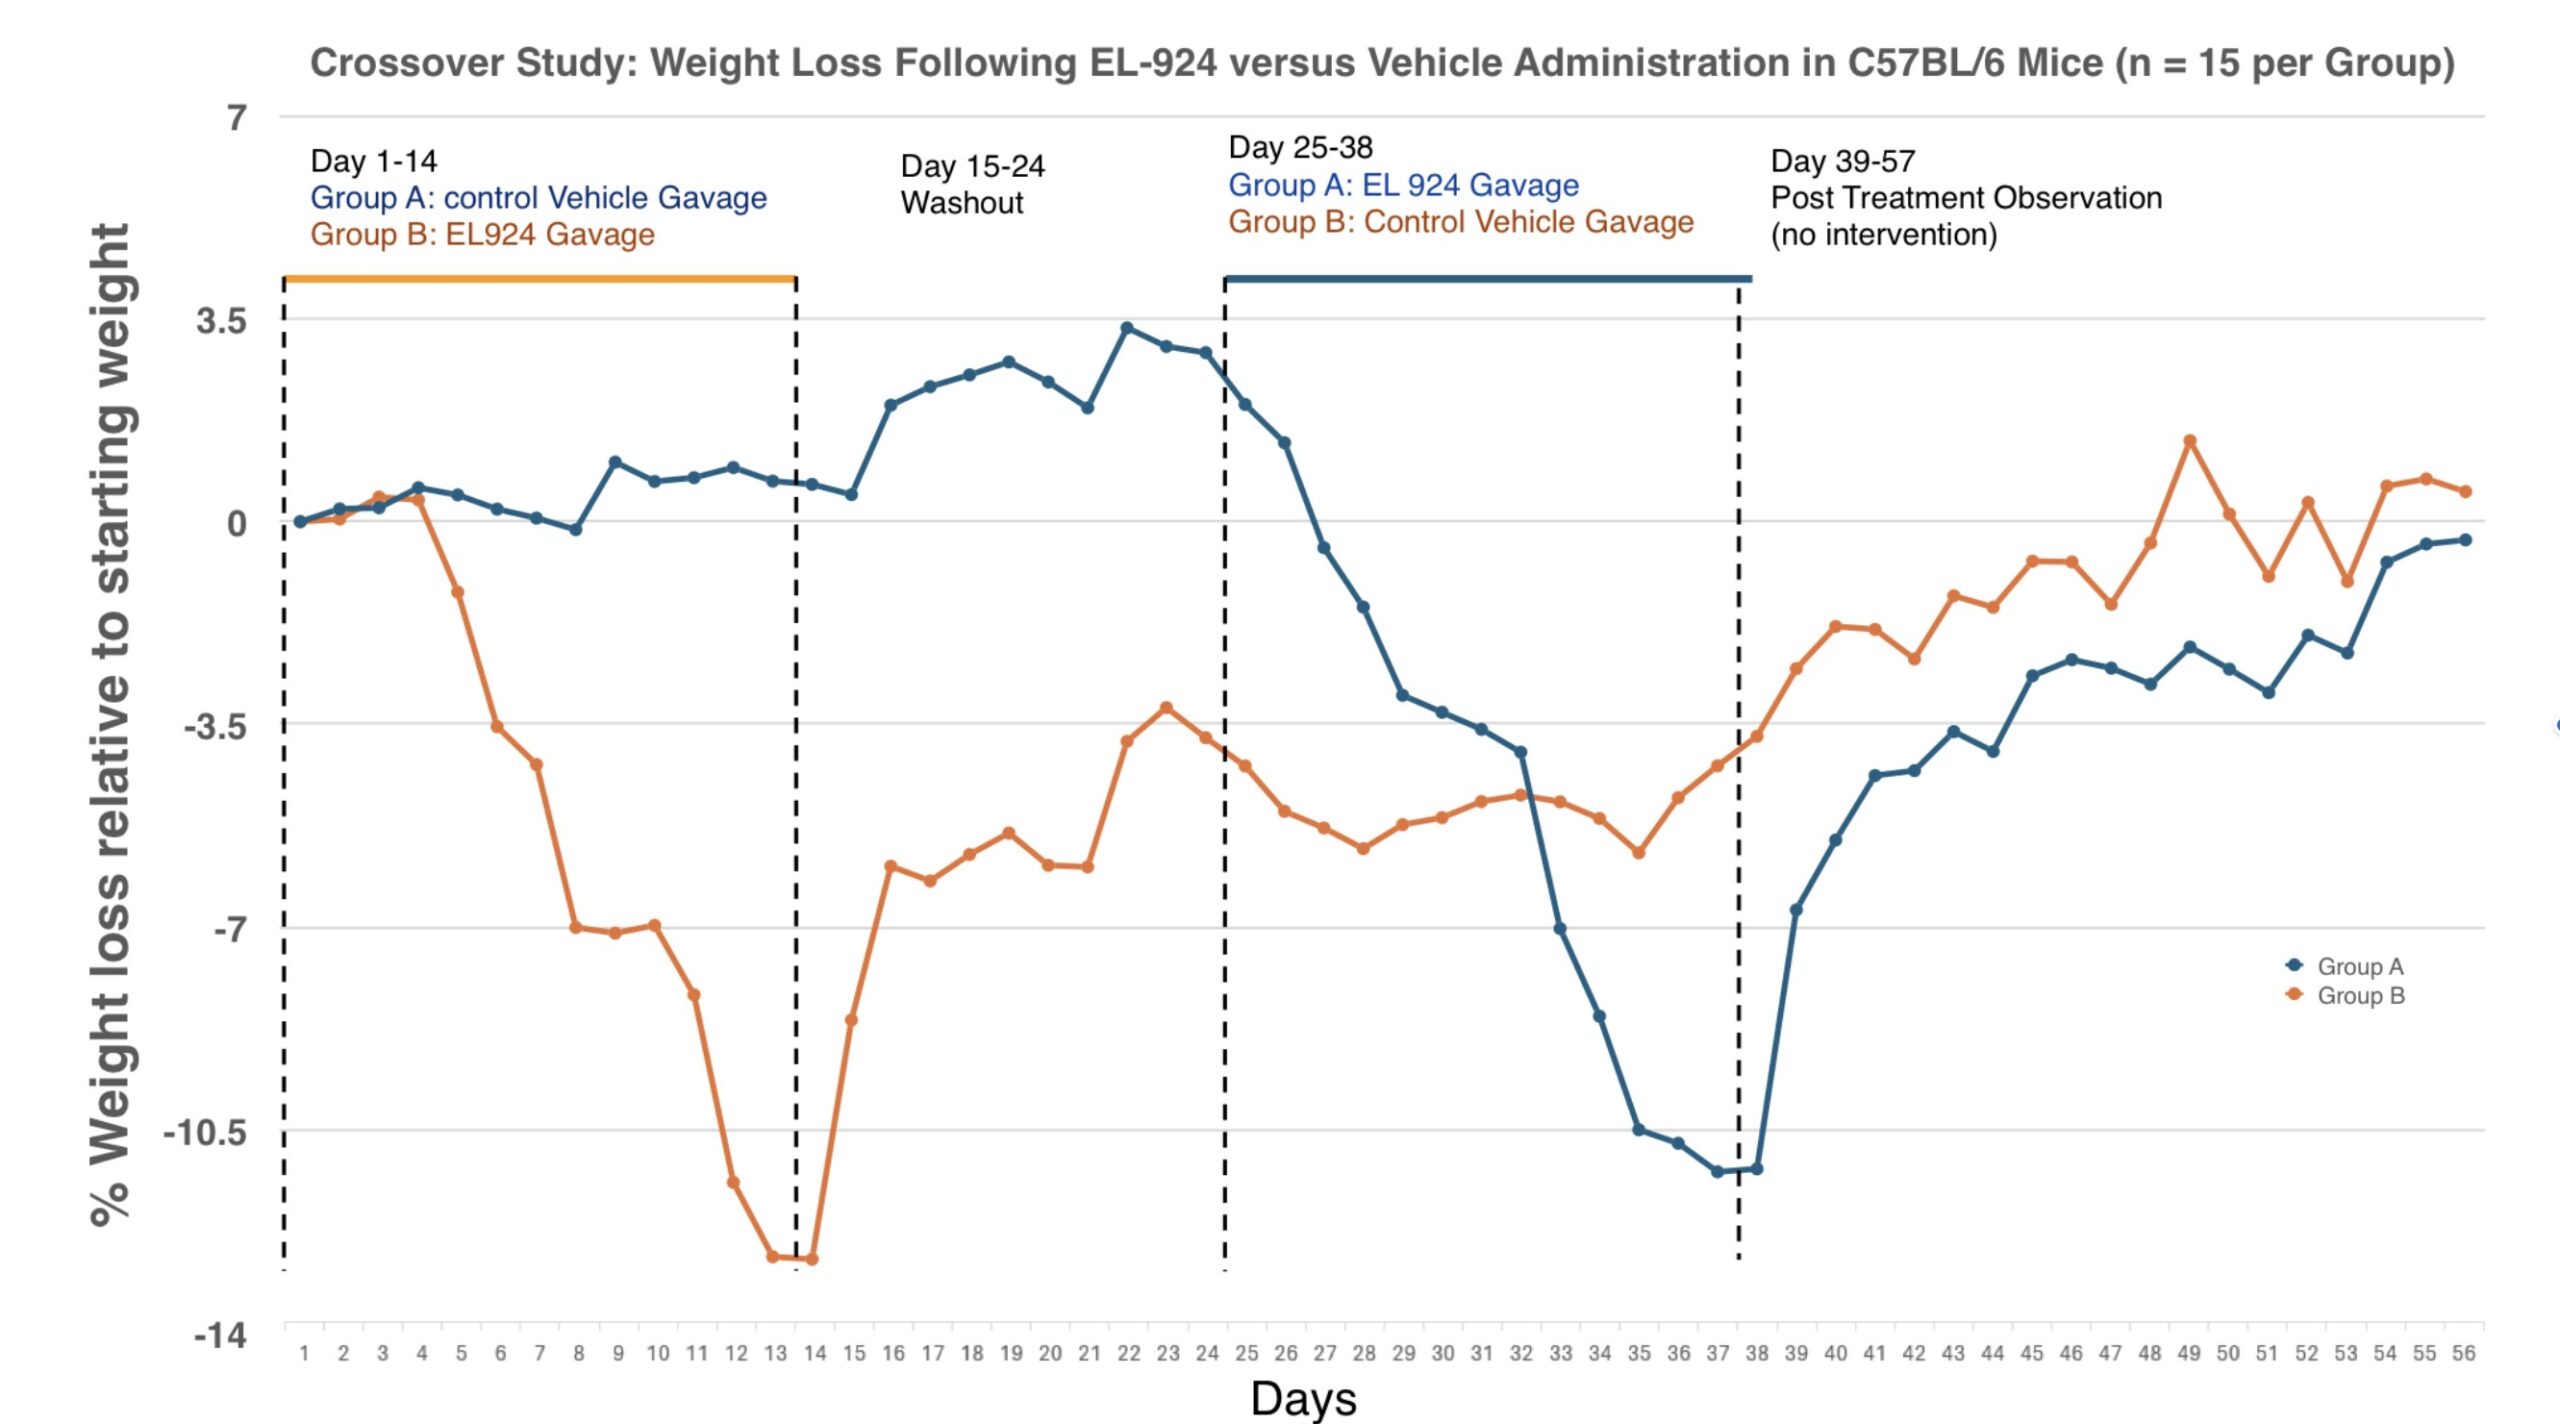
In our crossover experiment obese C57BL/6 mice, EL-924 produced approximately 12 % weight loss within two weeks, with the effect reproduced following crossover.
Importantly, weight loss occurred without reduced food intake or altered feeding behavior, and without observed diarrhea, bloating, feeding discomfort, or other toxicity signals.
This pattern supports a mechanism distinct from appetite suppression and a favorable GI tolerability profile in these preclinical studies.
A Signal of Post-Treatment Durability
Following treatment discontinuation, partial weight regain occurred rapidly; however, a residual weight-loss effect persisted for approximately three times the duration of active treatment.
Early Human Observations with EL-924
Limited, non-pivotal, real-world observations N2
EARLY REAL-WORLD HUMAN OBSERVATIONS — HYPOTHESIS-GENERATING ONLY — SUGGEST A MULTI-DOMAIN, “METABOLIC-HEALTH-FIRST” RESPONSE
In two non-pivotal, uncontrolled human observations, including use for up to 18 months without an observed toxicity signal, EL-924 showed hypothesis-generating changes across multiple metabolically linked domains.
In the most extensively characterized participant 47 y/o with obesity, prediabetes, metabolic dysfunction and marked insulin resistance, the pattern was notable for both its speed and breadth:
~3 WEEKS — INSULIN RESISTANCE IMPROVED RAPIDLY
HOMA-%S 24% → 72% (~3×) | HOMA-IR 4.2 → 1.4 | Weight ~−3%
Estimated insulin sensitivity moved toward the normal reference range before substantial weight loss by week 3.
~7 WEEKS — BROADER METABOLIC IMPROVEMENT EMERGED
TG ↓~62% | TG/HDL ↓~67% | Adiponectin/Leptin ↑~100% | Testosterone ↑~86% | SHBG ↑~105%
~17 WEEKS — METABOLIC IMPROVEMENT DEEPENED
HOMA-%S reached 117% of the young-adult reference | HOMA-IR ↓~80% | TG ↓~66% | TG/HDL ↓~74% | Adiponectin/Leptin ↑~267%
Weight loss reached ~14%, with measured lean mass preserved.
METABOLIC HEALTH FIRST. WEIGHT LOSS FOLLOWED.
Marked metabolic dysfunction → rapid improvement in insulin sensitivity → broader multi-domain metabolic improvement → substantial weight loss with preserved lean mass
The participant also reported marked improvements in energy, strength and exercise performance, occurring alongside the metabolic changes. These observations are directionally consistent with the hypothesis of improved energy handling and metabolic flexibility, processes closely linked to insulin sensitivity and mitochondrial function.
The temporal pattern resembles an important feature of metabolic surgery, where metabolic improvements can occur rapidly and precede substantial weight loss.
A DIFFERENT THERAPEUTIC SEQUENCE
Multi-Domain Metabolic Improvement → Improved Energy Handling & Metabolic Flexibility → Weight Loss With Preserved Function
These observations are uncontrolled and hypothesis-generating and do not establish safety, causality or efficacy. Metabolic flexibility and mitochondrial function were not directly measured. Findings require confirmation in prospective controlled clinical studies.
WHERE EL-924 MAY FIT IN THE EVOLVING OBESITY TREATMENT LANDSCAPE
This creates potential for:
Potential Role in the Obesity Treatment Ecosystem
A key differentiator for EL-924 is that preclinical weight loss was observed without reduced food intake, altered feeding behavior, signs of feeding discomfort, or significant stool changes.
Early human observations also suggest good tolerability and rapid improvement in insulin resistance before substantial weight loss, supporting a mechanism distinct from appetite suppression.
Next-generation incretin therapies may achieve greater maximal weight loss, but tolerability, lean-mass preservation, long-term persistence, and dependence on chronic appetite suppression remain important considerations.
EL-924 is being developed as a differentiated option for patients in whom metabolic benefit, tolerability, preservation of lean mass and physical function, and maintenance of normal eating behavior may be particularly important.
Its distinct mechanism may also create opportunities for complementary use with incretin-based therapies.
Sarcopenic obesity, where preservation of lean mass and nutrition status is clinically important
Stand-alone use in patients who cannot tolerate incretin-based therapies
Stand-alone use in patients seeking weight loss without severe restriction of eating behavior, social life, lean mass loss, or performance limitations
Combination therapy with GLP-1/GIP or other incretin-based agents to induced greater weight loss
Lower-dose incretin combinations to improve tolerability when continuation of incretin-based therapy is desirable
Weight-loss maintenance after discontinuation of appetite-suppressive therapy, potentially allowing patients to return to more normal eating patterns with reduced risk of weight regain
Potential benefit beyond obesity: Approximately 20-30% of normal-weight adults may have a metabolically unhealthy phenotype
Lean Mass Preservation
Lean-Mass Preservation
Early observations with EL-924 suggest preservation of lean mass during weight loss, potentially reflecting its distinct, non-appetite-suppressive mechanism.
Gastric bypass produces substantial lean-mass loss despite very favorable changes in metabolic and anabolic signaling, likely influenced by the profound caloric restriction accompanying early postoperative weight loss. In contrast, ileal transposition alters intestinal nutrient and hormonal signaling without gastric restriction; in animal studies, it reduced adiposity while largely preserving lean mass.
Similarly, EL-924 produced weight loss in preclinical studies without reduced food intake, potentially avoiding calorie-deficit signals that contribute to lean-mass loss.
The mechanism remains under investigation. If confirmed clinically, lean-mass preservation could represent an important differentiator for EL-924.
Advancing GI-Directed Metabolic Therapy Beyond First-Generation Approaches
Engineered to address key translational limitations of earlier polymer-based approaches—with the potential to become a differentiated therapy within the emerging class of GI-directed metabolic therapeutics.
Multiple independent groups have demonstrated in preclinical models and early human studies that targeting the intestinal nutrient interface with polymer technology can produce rapid and substantial metabolic benefits. These findings provide important validation for the therapeutic potential of GI-directed modulation of nutrient signaling.
However, translating this biology into a practical, scalable therapy has remained challenging. Earlier approaches have faced limitations including modest weight-loss efficacy, gastrointestinal tolerability, relatively high material requirements that may translate into substantial pill burden, and dosing regimens requiring fasting or separation from meals.
Elaphron is engineering a next-generation approach designed to overcome these translational barriers.
In preclinical studies, EL-924 has demonstrated substantial metabolic and weight-loss effects at materially lower administered quantities than some previously reported approaches. Importantly, these effects were observed in animals with unrestricted access to food, feeding behavior didn’t change supporting the potential for less dependence on precisely timed administration relative to meals.
The platform has also been specifically engineered with gastrointestinal tolerability, lower material burden, and practical oral administration as core product-development objectives.
Together, these attributes support EL-924’s potential to advance GI-directed metabolic therapy toward a differentiated, scalable, and potentially best-in-class oral treatment for metabolic disease.
Limitations of Metabolic Surgery–Mimetic Approaches and Ways to Address Them
Variable response: Gut nutritional-signaling reprogramming may not work for every patient. Bariatric surgery, EndoBarrier, and epithelial resurfacing literature suggest meaningful responses in a Majority of patients (potentially 50-90%) but not for all, obesity is heterogeneous, with both non-responders and hyper-responders expected.
GI tolerability: Nutrient-diversion approaches can increase delivery of undigested nutrients to lower regions of the gut, which may trigger bloating, nausea, diarrhea, and lead to SIBO. Elaphron has worked to address this through targeted modifications to EL-924’s polymer design.
Absorption monitoring: Potential effects on vitamin, micronutrient, and drug absorption are valid concerns. No meaningful vitamin or micronutrient absorption issues have been observed in our prolonged-use human observational data, but this will remain an important area for clinical monitoring.
Broader Platform Validation
Our additional drug candidates EL-156 and EL-787 support the broader platform concept: by tuning local intestinal coating, epithelial interaction, and GI signaling, the same core technology can generate differentiated therapies across metabolic, inflammatory, functional, and secretory GI diseases.